UTIs after menopause are driven by falling estrogen, not hygiene or behavior. What's actually changing, what the symptoms mean, and when to call a doctor.
You know the feeling. The sudden urgency, then the burning. Maybe blood in the toilet. A dull ache low in your abdomen.
Another one.
If you're postmenopausal and this keeps happening, the first thing worth knowing is that it is not a hygiene failure and it is not a consequence of anything you did. Urinary symptoms and recurrent UTIs become more common after menopause, and falling estrogen is one of the major reasons why.
The second thing worth knowing is that "hormonal" does not mean "nothing can be done." It means the thing to treat is different from what you've probably been offered.
Why Do UTIs Get More Common After Menopause?
Estrogen does several jobs in the urogenital tract, and it stops doing all of them at once.
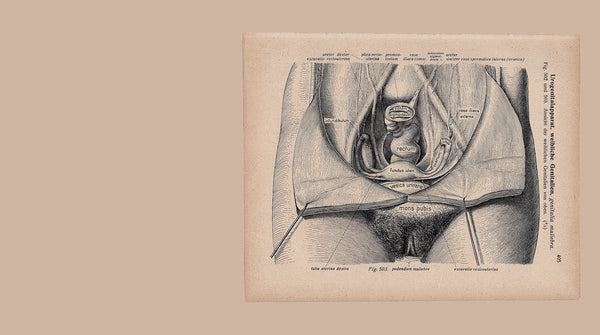
It keeps the tissue intact. Estrogen keeps vaginal and urethral tissue thick, elastic and moist. Without it, tissue thins and dries, and develops micro-tears that give bacteria an entry point.
It maintains the microbiome. Estrogen feeds the Lactobacillus that hold vaginal pH in the acidic 3.8 to 4.5 range and crowd out E. coli. After menopause, Lactobacillus populations fall, pH climbs toward 5.0 to 7.5, and the vaginal environment becomes more hospitable to uropathogens. That ecosystem doesn't start in the vagina either, which is its own conversation.
It supports the lower urinary tract. Estrogen receptors sit throughout urogenital tissue, including the urethra and bladder. After menopause those tissues change, and urinary symptoms and incomplete bladder emptying become more common. Residual urine matters because it gives bacteria more opportunity to multiply.
It feeds local immunity. Estrogen supports blood flow, immune cell activity and tissue repair. Less estrogen means fewer immune cells arriving and slower healing.
The same drop happens after ovary removal, during some cancer treatments, and on medications that suppress estrogen. The mechanism doesn't care how you got there.
This is structural, not behavioral. Which is why the fix has to be structural too.
Are UTIs After Menopause Caused by Something You're Doing?
Almost certainly not, and this is worth saying plainly because most women arrive at this question having already blamed themselves.
You do not get recurrent UTIs after menopause because you failed to wipe correctly, took a bath, wore the wrong underwear or forgot to pee immediately after sex.
Sexual activity is the one most women assume hardest, and the research in postmenopausal women is genuinely split. Some studies find an association, others find none. It is not the thing explaining your pattern.
What the research does consistently find, in postmenopausal women specifically, is a different set of factors: urinary incontinence, a history of UTIs before menopause, and nonsecretor status, which is an inherited trait affecting how your cells present to bacteria. Falling estrogen sits underneath all of it.
None of those are things you chose.
What Does a UTI Feel Like After Menopause?
The symptoms are the same as they have always been. Burning when you urinate. Sudden urgency. Needing to go often, especially at night. Urine that looks cloudy or dark or smells strong. Blood, which can look pink, red or brown. Pelvic pressure or a low ache. The sense that your bladder didn't fully empty.
What changes after menopause is how often it happens, and how easily it gets dismissed.
When Is a UTI an Emergency?
Call your doctor the same day if you have a fever or chills, severe pain in your back or side under the ribs, or nausea and vomiting alongside urinary symptoms.
That combination suggests the infection has reached your kidneys. Kidney infections do not wait, and they do not resolve on their own. Don't sit with this one.
What Does a Negative Urine Culture Actually Mean?
This catches a lot of women and almost nobody explains it.
Start with what a negative culture does and doesn't tell you. It does not necessarily mean there is no infection. Standard culture is less sensitive than most people assume: in a study of 220 women with typical UTI symptoms, culture found a uropathogen in 80.9%, while PCR found E. coli in 95.9% of the same women. Those participants averaged 38 years old, so the result doesn't transfer directly to postmenopausal women, but it establishes the principle. A negative culture is not proof that nothing is there.
The other possibility runs the opposite way. As estrogen falls, you can get the exact sensations of a UTI with no bacteria present at all. Burning, urgency, frequency, pressure, all from thin and irritated tissue rather than from an infection. Antibiotics do nothing in that case, because there is nothing to kill.
So repeated negative cultures alongside real symptoms should prompt evaluation for genitourinary syndrome of menopause and other noninfectious causes, and a harder look at whether the testing missed something. What they should not trigger is another reflexive antibiotic course, which disrupts a microbiome already under strain and answers neither question.
What Else Should Your Doctor Rule Out?
Because urologic factors carry real weight in postmenopausal women, a few things are worth checking if the infections keep coming:
Incomplete bladder emptying, which can be measured with a simple post-void scan. Pelvic organ prolapse, including cystocele. Urinary incontinence. Diabetes or prediabetes. Kidney stones.
None of these is common enough to assume, and all of them are common enough to check. If you've had three or more infections in a year and nobody has looked at any of this, that's the gap.
What Should You Do About Recurrent UTIs After Menopause?
The first step is to address the estrogen loss that changed the urinary environment in the first place. The 2025 AUA guideline recommends vaginal estrogen for postmenopausal women with recurrent UTIs when there is no contraindication. Our guide to Vaginal Estrogen for UTI Prevention covers how it works, the three forms, safety and what to ask your doctor.
Estrogen doesn't address every part of recurrence, however. Bacterial exposure and adhesion are a separate part of the problem, which is why non-antibiotic prevention may be used alongside it.
If you're looking for the actual prevention plan, including vaginal estrogen, bacterial anti-adhesion strategies, antibiotics and what to do during the first twelve weeks, read Recurrent UTIs in Perimenopause & Menopause: Why Prevention Needs a Dual Strategy.
Where to Start
Book the appointment. Bring your numbers, meaning how many infections in the past six and twelve months, what was cultured, and what you've already tried. The Perimenopause & Menopause UTI Tracker is built for exactly this, and ten minutes with it beats trying to remember in the room.
Then ask about vaginal estrogen by name. Our UTI Appointment Script has the wording if you'd rather not improvise. If you're told this is just part of getting older, that is not a clinical finding. Ask for a referral to a urogynecologist or a Menopause Society Certified Practitioner. The American Urogynecologic Society lists providers at augs.org, and certified practitioners are listed at menopause.org.
You have had this explained to you as bad luck or bad hygiene for long enough. It is neither.
FAQ
Frequently Asked Questions
Why are UTIs more common after menopause?
Estrogen maintains the tissue, pH and microbiome of the urogenital tract. As estrogen falls, vaginal and urethral tissue thins, Lactobacillus populations decline, pH rises from the acidic 3.5 to 4.5 range toward 5.0 to 7.5, and local immune activity drops. E. coli has an easier path in and the body has less natural defense against it. In the Raz and Stamm trial, restoring estrogen locally brought vaginal pH back down from 5.5 to 3.8 and cut infections from 5.9 to 0.5 per patient-year.
Can UTIs start years after menopause?
Yes. The genitourinary changes caused by estrogen loss do not peak when your periods stop. Unlike hot flashes, which often improve with time, genitourinary syndrome of menopause is chronic and progressive, and its prevalence rises with years since menopause. In the AGATA study of 913 postmenopausal women, GSM was identified in 64.7% of women one year after menopause and 84.2% six years after. Urinary symptoms, including recurrent UTIs, are part of GSM. So urinary problems arriving well after your final period are not a sign that something new has gone wrong.
Are UTIs after menopause caused by poor hygiene?
No. You do not get recurrent UTIs after menopause because of wiping technique, baths, underwear choice or how soon you urinate after sex. Sexual activity is the one most women assume, and the research in postmenopausal women is genuinely split. What the evidence does consistently identify is urinary incontinence, a history of UTIs before menopause, and nonsecretor status, with falling estrogen underneath all of it.
Can you have UTI symptoms with a negative culture after menopause?
Yes, and there are two very different explanations. A negative standard culture does not necessarily mean there is no infection: in a study of 220 women with UTI symptoms, culture was positive in 80.9% while PCR found E. coli in 95.9%, though those participants averaged 38 years old. The other explanation is that falling estrogen leaves thin irritated tissue producing burning, urgency, frequency and pressure with no bacteria present, in which case antibiotics do nothing. Repeated negative cultures alongside real symptoms should prompt evaluation for genitourinary syndrome of menopause and other noninfectious causes, not another reflexive prescription.
When should you go to the doctor for a UTI after menopause?
Call the same day if you have fever or chills, severe back or side pain under the ribs, or nausea and vomiting alongside urinary symptoms. That combination suggests the infection has reached your kidneys, which requires prompt treatment. Otherwise, any infection pattern of two or more in six months or three or more in twelve months warrants a prevention conversation rather than another round of antibiotics.
What should my doctor rule out if UTIs keep coming back?
Incomplete bladder emptying, which a post-void residual scan measures in minutes. Pelvic organ prolapse including cystocele. Urinary incontinence. Diabetes or prediabetes. Kidney stones. Urologic factors carry real weight in postmenopausal women, and if you have had three or more infections in a year without any of this being examined, that is the gap in your care.
Is vaginal estrogen safe for breast cancer survivors?
Many survivors are candidates, but this is a conversation for your oncologist rather than your primary care provider. Low-dose vaginal estrogen produces minimal systemic absorption, and both the American College of Obstetricians and Gynecologists and The Menopause Society support considering it when local symptoms are significantly affecting quality of life. Ask directly rather than assuming the answer is no.